
What Is medical Detox and How It Works
Reviewed by clinical staff
Published September 6, 2026 · Updated September 17, 2026

Contents
You may be asking yourself this after another difficult night: should you stop using at home, wait until withdrawal begins, or call a detox program now? Fear often centers on the symptoms, but the more important question is how much medical risk your withdrawal may carry and what support you'll need afterward.
medical detox is a structured clinical service for managing withdrawal safely. It isn't a private room where you stop using, and it isn't a complete cure for substance use disorder. It's the first stage of care, designed to reduce immediate danger, stabilize your body and mind, and help you move into treatment that addresses recovery over time.
What medical Detox Actually Means
medical detox is withdrawal management provided by trained clinical staff who assess your condition, monitor changes, and respond when symptoms become more serious. Depending on your needs, care may involve physicians, nurses, addiction specialists, counselors, and other professionals. The team tracks vital signs, evaluates mental health, supports hydration and nutrition, and may use medications to control withdrawal symptoms.
That differs sharply from quitting alone. At home, a person may not recognize when shaking has progressed into a dangerous alcohol withdrawal syndrome, or when confusion, severe agitation, sedation, or breathing changes require emergency care. Over-the-counter products can't replace a clinical assessment, a medication plan, or monitoring for complications.
Practical rule: The safety question comes before the comfort question. A clinician must first determine whether your withdrawal can be managed outside a 24-hour setting.
Detox is a process, not a cure
The SAMHSA Treatment Improvement Protocol framework defines detoxification through evaluation, stabilization, and fostering entry into treatment. It also says patients should be assessed for suicide risk during detox. That makes clear that detox is a medically monitored intervention, not just "stopping use" and waiting for symptoms to pass.
A team may ask what substance you've used, when you last used it, how much and how often you used, whether other substances are involved, and whether you've experienced seizures, hallucinations, severe confusion, or previous failed withdrawal attempts. Clinicians also review medical conditions, prescribed medications, pregnancy status when relevant, and psychiatric symptoms.
The immediate goal is physical and psychological stabilization. Once you're stable enough to participate in the next level of care, the team helps arrange residential treatment, outpatient services, or medication treatment. Detox can open the door to recovery, but it doesn't address every reason substance use began or every skill needed to maintain recovery.
The Three Clinical Phases of Detox
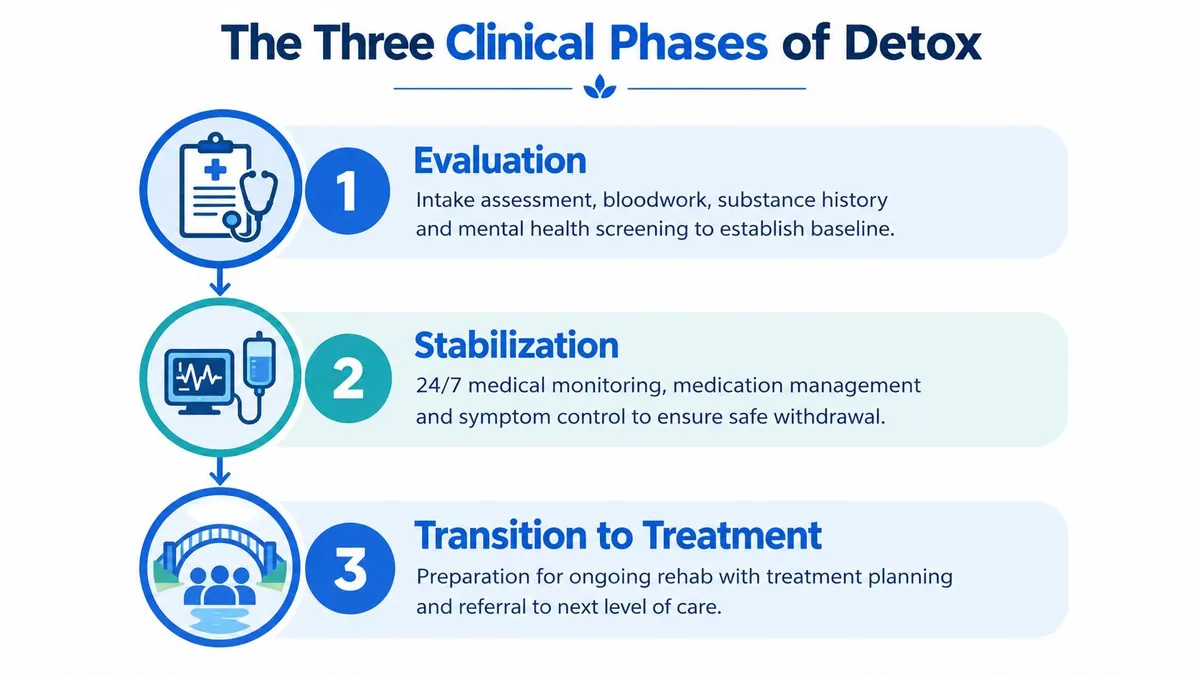
Modern withdrawal management follows a connected sequence rather than a single event. The phases described in SAMHSA's detoxification guidance are evaluation, stabilization, and fostering readiness for ongoing treatment.
Evaluation identifies the risks
During intake, clinicians establish a baseline. They may record vital signs, complete laboratory testing when indicated, review substance use and medical history, screen for mental health concerns, and assess hydration, nutrition, sleep, and recent medication use.
This information guides the setting and the treatment plan. Someone withdrawing from alcohol with a prior withdrawal seizure needs a different level of observation from someone with mild symptoms and reliable support at home. The evaluation also helps staff identify co-occurring depression, psychosis, suicidal thoughts, or medical problems that could complicate withdrawal.
Stabilization is active medical care
Stabilization is the period when withdrawal symptoms are monitored and treated. A nurse may check vital signs and withdrawal symptoms at scheduled intervals, while a physician adjusts medication according to the person's response. Staff may provide fluids, nutrition, a quieter environment, sleep support, reassurance, and symptom-targeted treatment.
The team isn't following a rigid script. If symptoms worsen, medication may be changed, monitoring may become more frequent, or the patient may need transfer to a higher-acuity setting. If sedation develops after medication, clinicians must respond promptly.
Readiness connects detox to recovery
The third phase begins before discharge. Counselors and medical staff discuss what happens next, explain treatment options, coordinate referrals, and identify barriers such as transportation, housing, family conflict, or untreated mental illness.
That planning matters because leaving after withdrawal ends without continuing care can leave a person vulnerable during a difficult transition. Detox is complete only when the patient is medically stable and has a realistic path toward ongoing treatment.
Alcohol Detox Explained · Watch on YouTube
Common Withdrawal Symptoms and Why Medical Care Matters
Withdrawal doesn't look the same for every substance. The substance class, amount and duration of use, physical health, co-occurring conditions, and previous withdrawal history all influence what happens after the last use.
Alcohol and benzodiazepines require particular caution. Abrupt alcohol withdrawal can involve seizures, delirium, and unstable autonomic function. Benzodiazepine withdrawal can also become medically dangerous, especially after prolonged or high-dose use. A person who has previously experienced severe withdrawal shouldn't assume the next attempt will be mild.
Opioid withdrawal commonly produces muscle aches, sweating, nausea, diarrhea, anxiety, restlessness, insomnia, and strong cravings. It's often intensely uncomfortable, even when it isn't usually fatal by itself. Medical treatment can reduce distress and help a person stay engaged in care.
Stimulant withdrawal may bring exhaustion, depressed mood, irritability, reduced motivation, and powerful cravings. Mental health monitoring matters because depression or suicidal thoughts can emerge during the crash and early withdrawal period. Clinicians also watch for dehydration, poor nutrition, unmanaged pain, confusion, and interactions involving multiple substances.
A clinical team can recognize a warning sign before a family member knows what it means. For a practical description of the experience, see what happens during detox. Seek urgent medical help for seizures, severe confusion, hallucinations, chest pain, trouble breathing, loss of consciousness, or thoughts of suicide.
Who Needs Inpatient Versus Outpatient Detox
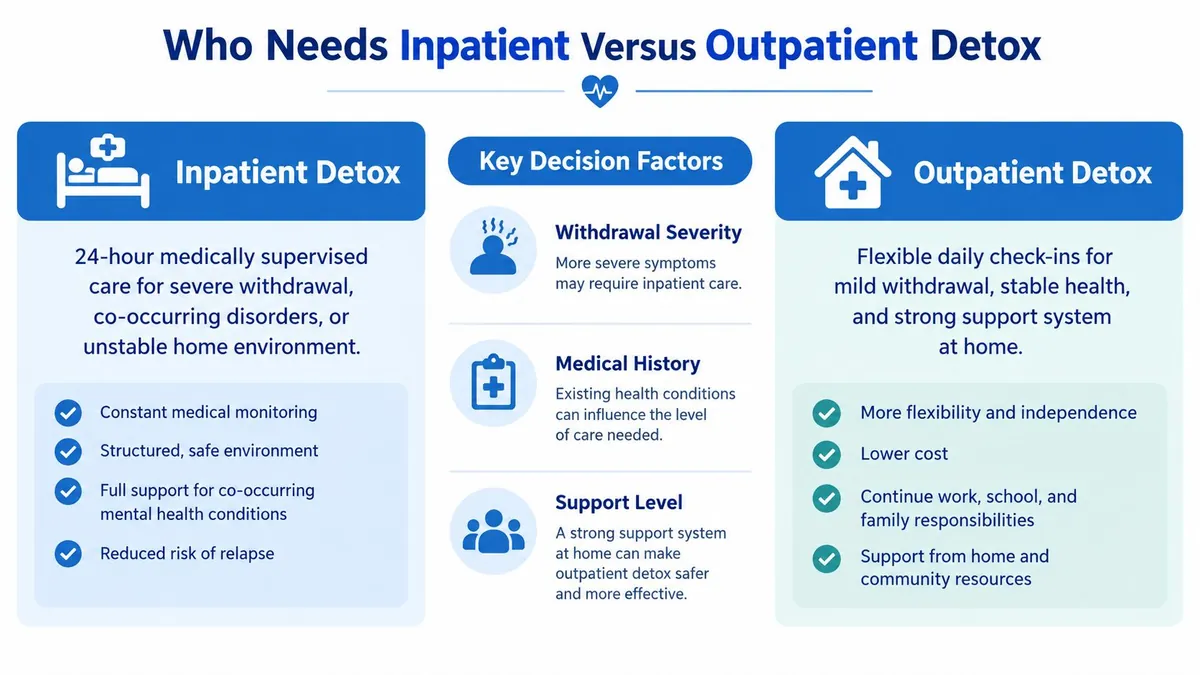
Not everyone needs a hospital bed or residential detox. The right choice depends on withdrawal risk, health history, psychiatric stability, available support, and the safety of the home environment. Convenience shouldn't determine the level of care, and neither should a blanket rule that sends everyone to the most intensive setting.
When 24-hour care is usually safer
Inpatient or 24-hour medical detox deserves serious consideration when a person has:
- High-risk alcohol withdrawal: Heavy daily alcohol use, previous withdrawal seizures, delirium, or rapidly escalating tremors.
- Benzodiazepine dependence: Long-term or high-dose use, especially with a history of severe withdrawal.
- Polysubstance exposure: Alcohol, opioids, benzodiazepines, or other sedatives used together can complicate assessment and medication decisions.
- Unstable health: Significant medical illness, pregnancy, severe dehydration, or uncontrolled pain.
- Psychiatric concerns: Suicidal thoughts, psychosis, severe depression, or an inability to remain safe.
- An unsafe setting: No reliable support, unstable housing, ready access to substances, or no way to attend follow-up appointments.
- Previous outpatient difficulty: An earlier attempt ended in worsening symptoms, continued use, or inability to follow the treatment plan.
A formal assessment should explain why a particular setting is recommended. Clinicians consider recent use, previous complications, vital signs, mental health, prescribed medications, and the ability to follow instructions.
When outpatient withdrawal management may fit
Outpatient care can be appropriate when symptoms are expected to be lower risk, the person is medically stable, and a safe adult or dependable support system can help at home. The person must also be able to attend scheduled evaluations, communicate changes quickly, avoid substances, and reach emergency care if the plan changes.
A good recommendation explains the risk factors behind the setting. You're entitled to ask what assessment led to that decision.
Outpatient care isn't "less serious." It places more responsibility on the patient, support network, and clinical team. If the person becomes confused, sedated, severely agitated, suicidal, or medically unstable, the plan must change immediately.
Typical Detox Timelines by Substance
Detox has a limited withdrawal-management window, but there isn't one universal schedule. The clinical guidance on opioid and alcohol withdrawal emphasizes structured treatment and follow-up, while individual timing depends on the substance, dose, duration of use, health, and combinations with other drugs.
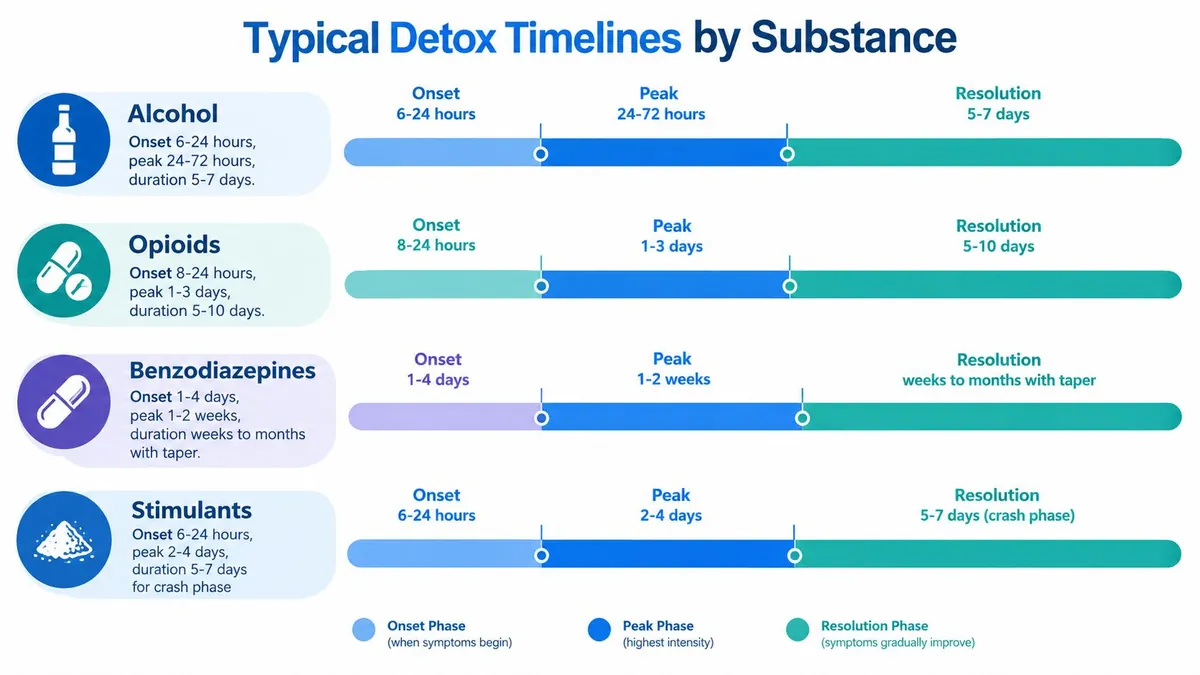
Alcohol withdrawal may begin within six to twenty-four hours after the last drink and become most intense within twenty-four to seventy-two hours, according to the clinical timeline provided in the treatment guidance. High-risk patients need close observation during this period because seizures or delirium can occur.
Short-acting benzodiazepines may produce symptoms within one to two days, while longer-acting medications can have a later onset and a more prolonged course. A taper may continue well beyond the first acute symptoms.
Short-acting opioid withdrawal may begin within eight to twenty-four hours. Symptoms often intensify around the third day and may resolve over the following days, although cravings and sleep disruption can last longer.
Stimulant withdrawal is usually less medically dangerous than alcohol or benzodiazepine withdrawal, but the emotional crash can be substantial. Depression, fatigue, and cravings may continue for weeks, making psychiatric observation and continuing treatment important.
For a fuller explanation of how timing varies, read how long detox takes. These ranges are guides, not promises. A treatment team adjusts care according to what your body is doing, not according to a calendar alone.
Insurance Coverage and Next Steps Into Treatment
The Mental Health Parity and Addiction Equity Act guidance supports parity between substance use treatment and medical or surgical benefits, while plans may still require authorization, documentation, or use of in-network providers.
Before admission, ask the program or insurer to clarify:
- Network status: Is the facility in network, and what changes if it's out of network?
- Medical necessity: What assessment and clinical records does the plan require?
- Patient costs: What deductible, copayment, coinsurance, or out-of-pocket responsibility may apply?
- Authorization: Who requests approval, and what happens if the insurer approves a shorter stay?
- Continuing care: Does coverage include residential care, partial hospitalization, intensive outpatient treatment, or medication treatment?
Coverage verification can be handled confidentially. A facility's admissions team may help interpret benefits, but you should still request the plan's explanation of coverage and ask what services are authorized.
Discharge planning should start during stabilization. Clinicians assess the appropriate next level of care using clinical criteria, then coordinate residential treatment, partial hospitalization, intensive outpatient care, outpatient counseling, or ongoing medication treatment.
Ask the provider how it handles referrals, prescriptions, transportation, family involvement, and aftercare. A clear answer shows that detox is being treated as the beginning of a care plan, not an isolated service.
What to Remember Before You Start
Withdrawal from alcohol, benzodiazepines, and some combinations of substances can become dangerous without medical supervision. Don't decide that home detox is safe because a previous attempt seemed manageable. Your current use pattern, health, medications, mental state, and withdrawal history all matter.
Detox is a stabilization bridge, not complete addiction treatment. Medication may begin during withdrawal management and continue afterward, particularly for opioid use disorder. Once your body is stable, the next recommendation may include residential treatment, partial hospitalization, intensive outpatient care, outpatient counseling, or ongoing medication treatment.
Insurance may cover detox when it's medically necessary, but you'll need to verify benefits and understand authorization requirements. Calling an admissions line is a confidential, non-binding way to ask about risk, medications, setting, costs, and next steps. You're gathering information, not signing away your choices.
Recovery develops over time. medical detox is the first safer chapter, and the right team can help you move from surviving withdrawal to building a practical plan for lasting care.
If withdrawal symptoms become severe, such as a seizure, severe confusion, hallucinations, chest pain or trouble breathing, call 911 or go to the nearest emergency room. If you or someone you love is in crisis or thinking about suicide, call or text 988.
Learn more about our outpatient addiction treatment services, or contact Addiction Resource Center.
Talk with us
Addiction Resource Center offers intensive outpatient treatment (IOP) for adults 18+ at our Yuba City office or by telehealth. If you need detox or residential care first, we coordinate it with our partner, Ona Treatment Center in Browns Valley, CA. Call or text 530-625-7910.
Check my insurance